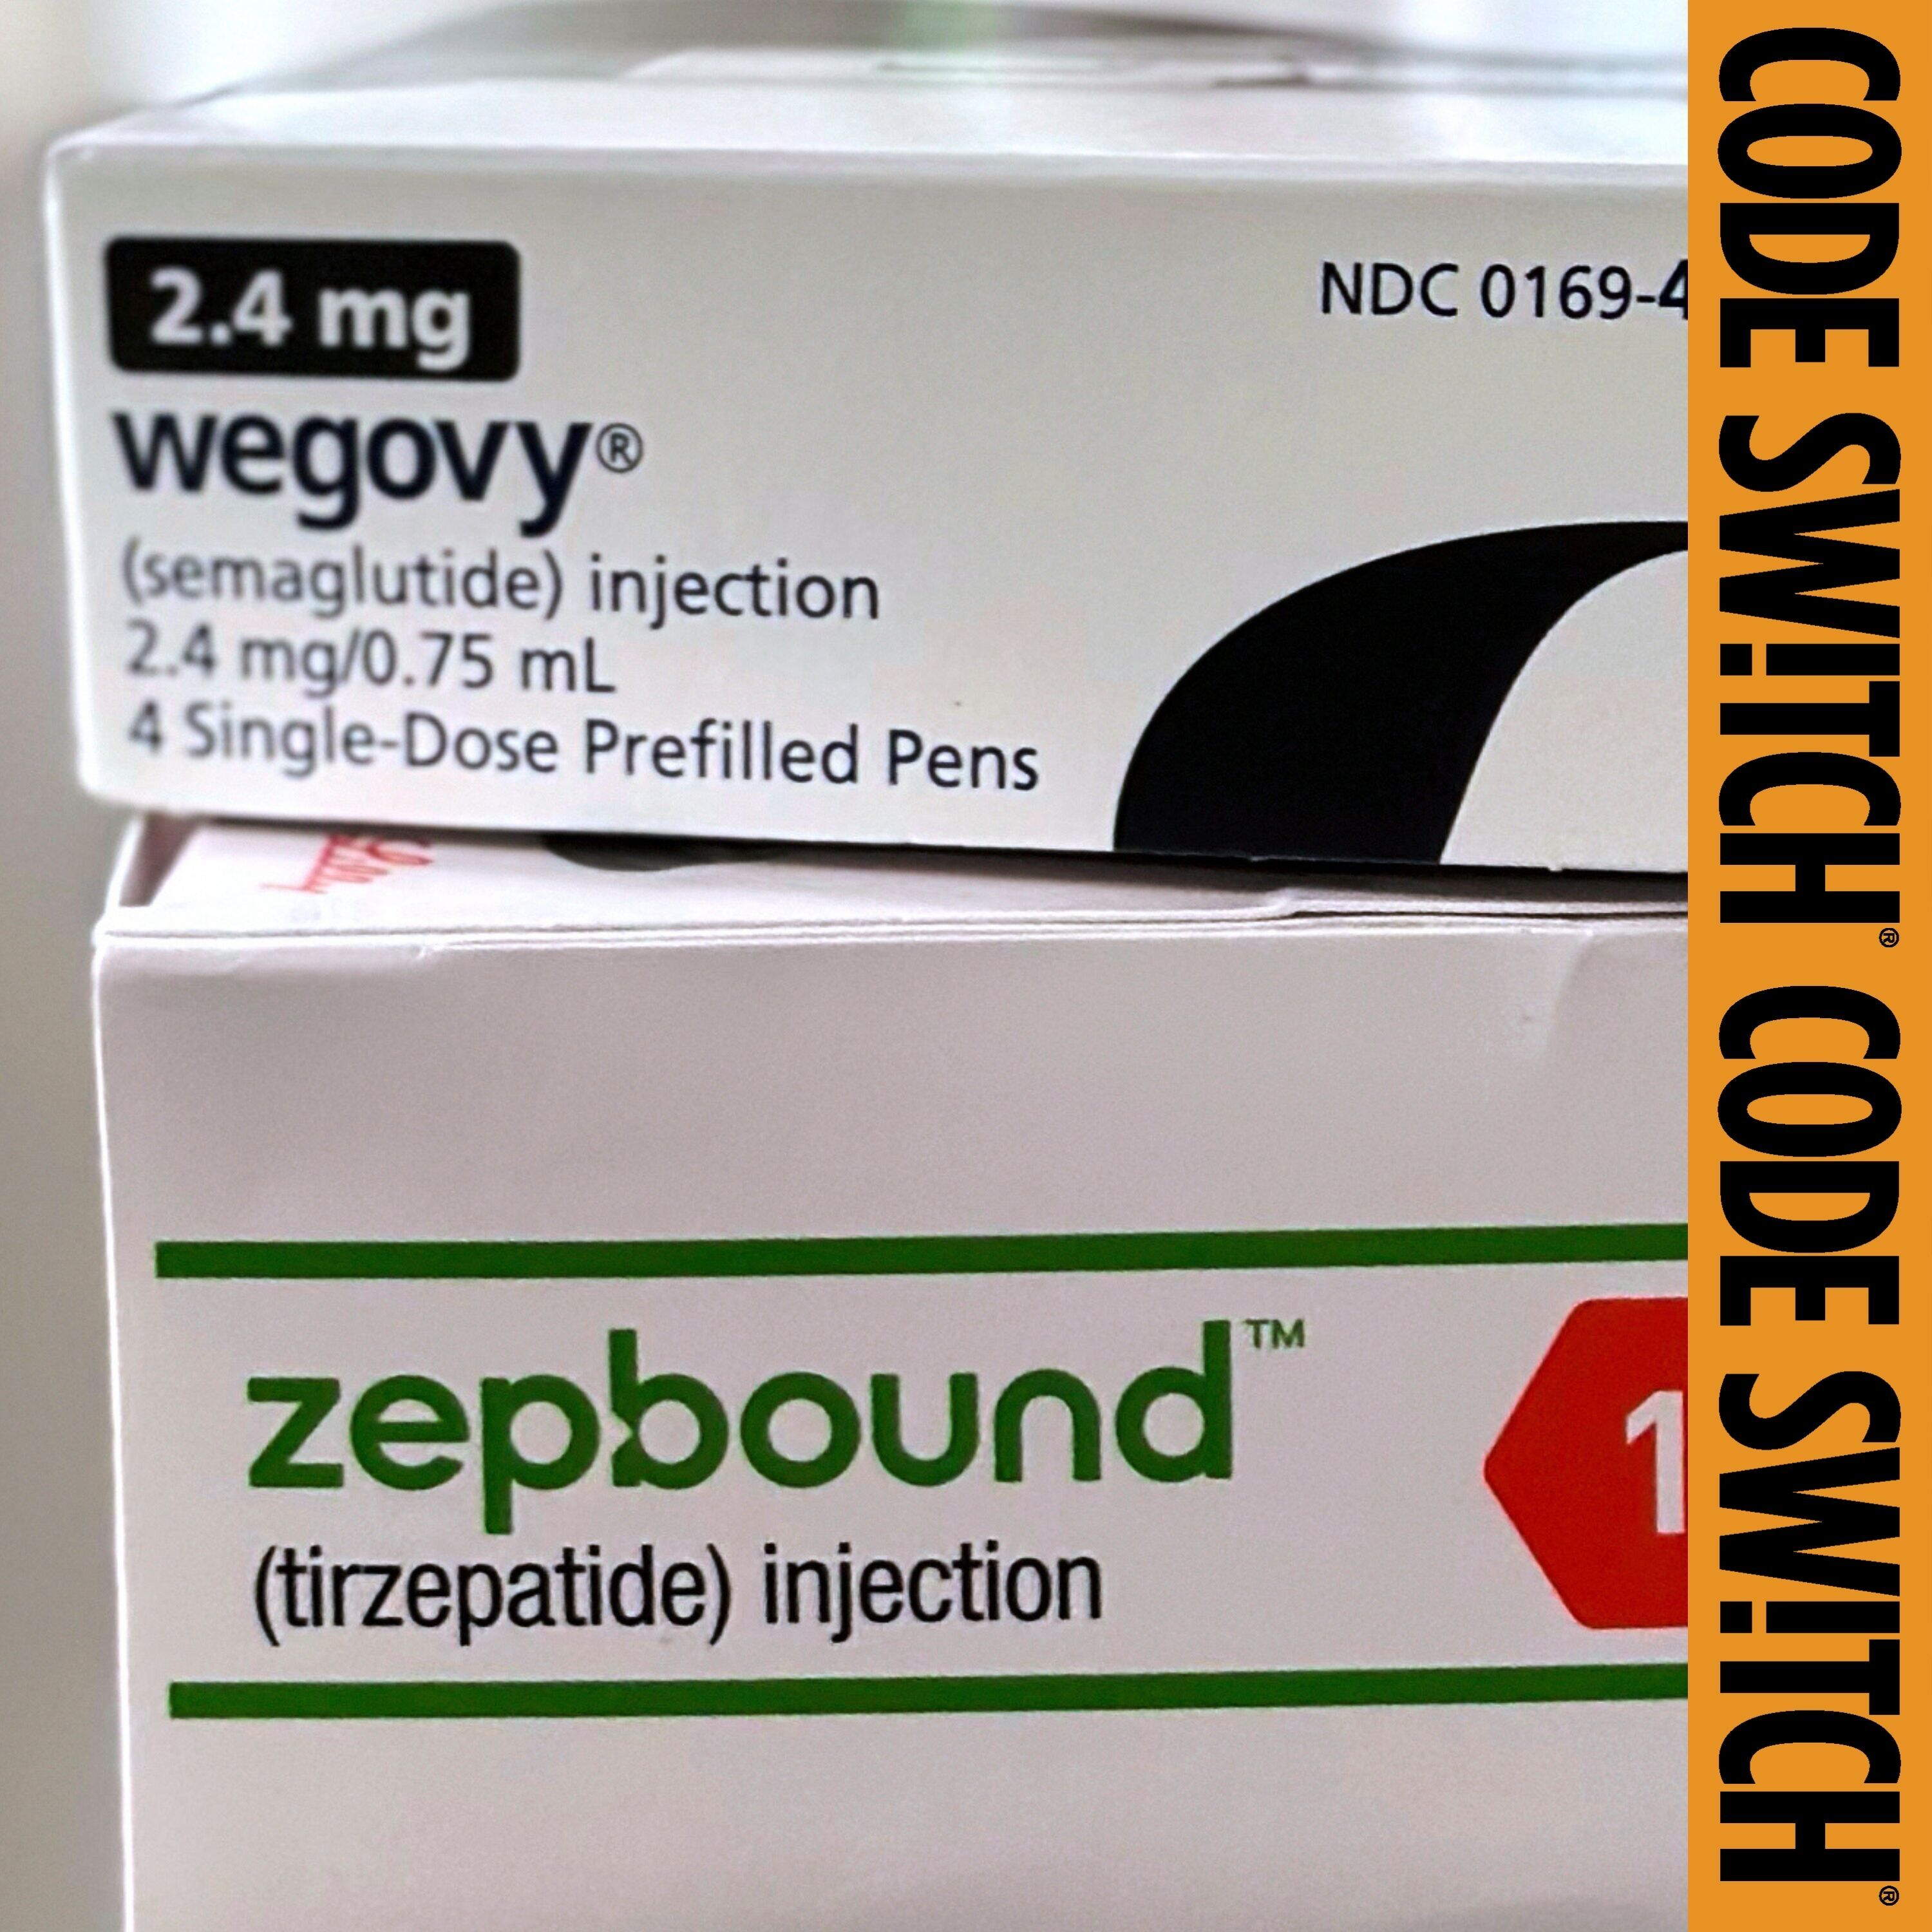
Overview of Freedom from fatness: Why GLP-1s go after Black bodies
This Code Switch episode examines the explosion of GLP-1 weight-loss drugs like Ozempic and Wegovy, with a focus on why so much of the marketing seems aimed at Black women. Hosts B.A. Parker and Jean Demby talk with sociologist and author Sabrina Strings (Fearing the Black Body) about the racial history of fatphobia, how modern GLP-1 advertising borrows from older anti-fat narratives, and why weight loss is often framed as both a health goal and a moral virtue. The episode argues that these drugs are being sold not just as medicine, but as a way to “solve” stigma—especially for Black women who have long been targeted by body shaming in medicine and popular culture.
Key Takeaways
- GLP-1s are everywhere now. What began as a diabetes medication has quickly become a mass-market weight-loss product and a huge cultural talking point.
- Marketing disproportionately centers Black women. The episode highlights ads featuring Black women, including celebrity endorsements and AI-generated imagery, and asks why Black bodies are so often used to sell weight loss.
- Fatphobia has deep racial roots. Sabrina Strings explains that modern obesity discourse is tied to centuries-old ideas about race, morality, and social hierarchy.
- Weight loss is sold as health, confidence, and redemption. Ads rarely promise only weight loss; they also imply better self-esteem, sex appeal, social approval, and moral improvement.
- Body size is deeply tied to class and access. GLP-1 use is shaped by whether someone can afford the medication, access healthcare, and receive a prescription in the first place.
- Structural problems are being framed as individual solutions. The episode pushes back on the idea that shrinking bodies can fix racism, health inequity, or stigma.
Why GLP-1 Ads Are Targeting Black Women
Black women as the “face” of weight-loss culture
Sabrina Strings argues that pharmaceutical companies often present Black women in GLP-1 ads to suggest that the drugs are a kind of remedy for the harms Black people have faced in medicine. The implication is: if Black people have been excluded from care, access to weight-loss drugs will somehow make that right.
The episode treats this as deeply cynical:
- It reframes historical medical neglect as a sales pitch.
- It suggests weight loss is a form of liberation or “repair.”
- It turns Black women’s vulnerability to stigma into a marketing opportunity.
Celebrity examples and public pressure
The discussion uses public figures like:
- Serena Williams, whose endorsement of a GLP-1 is seen as a response to years of public scrutiny over her body.
- Lizzo, whose relationship to body positivity made her own weight loss feel, to some fans, like a betrayal.
- Oprah, whose long public journey with weight has often been framed through repentance and redemption.
The point isn’t to shame these women, but to show how even powerful Black women are still subjected to intense body policing.
The History Behind Fatphobia
BMI’s strange origins
One of the episode’s most striking points is that BMI was not created by a physician. It traces back to:
- Adolphe Quetelet, a Belgian astronomer/statistician
- Later adoption by eugenicists like Charles Davenport
- Rebranding by Ancel Keys, who helped normalize BMI in medicine
The episode uses this history to show that BMI is not a neutral health measure—it emerged from systems interested in categorizing and controlling bodies, especially along racial lines.
Fatness as moral failure
Sabrina Strings explains that Western culture has long treated fatness as a sign of:
- laziness
- lack of discipline
- personal failure
- moral weakness
GLP-1s don’t remove that stigma; they often just repackage it. Now the “good” person is the one who loses weight the “right” way—through medicine, discipline, or enough money.
Health, Stigma, and the Limits of “Just Lose Weight”
Weight loss is not the same as health
The episode stresses that:
- Thinness does not automatically mean wellness.
- Chronic illnesses can affect people at any size.
- Losing weight does not solve racism, poverty, poor healthcare, or structural inequality.
Weight stigma can worsen health outcomes
Because doctors often over-focus on body size:
- Fat patients may delay care or avoid doctors.
- Real conditions, including cancer, can be missed.
- Black patients in particular report high levels of weight stigma in medical settings.
The episode makes the case that weight stigma can directly lead to worse medical care.
Class, Access, and Who Gets to Be “Healthy”
GLP-1s are expensive and unevenly accessible
The conversation points out the huge gap between:
- low monthly costs with insurance or a prescription
- versus very high out-of-pocket prices without coverage
That means body size increasingly reflects class privilege:
- Higher-income people may have easier access to prescriptions.
- Women, especially, are more likely to seek care and be prescribed these medications.
- Poorer people and people with less access to healthcare are less likely to benefit.
Thinness as a class marker
The episode suggests that, in today’s GLP-1 era, shrinking bodies can increasingly signal not just health, but also access, money, and medical attention.
Why It’s So Hard to Talk About Bodies Without Shame
Social media rewards reaction, not reflection
The hosts note the contrast between:
- fat-acceptance and fat-liberation creators
- public commentary on celebrities’ weight loss
- constant GLP-1 advertising
Their point: social media is built to provoke instinctive reactions, not thoughtful discussion.
Community matters
Sabrina Strings recommends seeking out informed voices and communities rather than relying on algorithmic feeds. The episode names examples like:
- fat liberation and body-positive educators
- online communities and organizations centered on fat justice
Notable Insight
“Weight loss is not reparations.”
That line captures the episode’s core argument: pharmaceutical solutions cannot substitute for compassion, equitable healthcare, or the dismantling of fatphobia.
Bottom Line
This episode argues that the GLP-1 boom is about much more than medication. It reflects a larger culture that:
- racializes fatness,
- monetizes shame,
- mistakes thinness for virtue,
- and sells body transformation as a cure for structural harm.
The strongest takeaway is that body size is never just personal. It is shaped by history, race, gender, class, healthcare access, and a long tradition of treating fat bodies—especially Black women’s bodies—as problems to be managed.